CERVICOGENIC HEADACHE: Causes and Treatment
CERVICOGENIC HEADACHE
What is cervicogenic headache (CGH)?
A cervicogenic headache presents as unilateral pain that starts in the neck and is referred from bony structures or soft tissues in the cervical spine. It is a common chronic and recurrent headache that usually starts after neck movement. It is usually accompanied by reduced range of movement of the neck. It could be often confused with migraine, tension headache or other primary headache syndromes. Diagnostic criteria must include all of the following points:
- The source of pain must be in the neck and perceived in the head or face.
- There must be evidence that the pain can be attributed to the neck. It must have one of the following:
- Demonstration of clinical signs implicating a source of pain in the neck or
- Abolition of a headache following diagnostic blockade of a cervical structure or its nerve supply using a placebo or other adequate controls.
- Pain resolves within 3 months after successfully treating the causative disorder or lesion.
What is the pathophysiology of CGH?
CGH is thought to be referred pain arising from irritation caused by cervical structures innervated by spinal nerves C1, C2 and C3. Therefore, any structure innervated by the C1-C3 spinal nerves could be the source of CGH.
The C1-C3 nerves relay pain signals to the nociceptive nucleus of the head and neck, the trigeminocervical nucleus. This connection is thought to cause referred pain to the occiput and/or eyes. Aseptic inflammation and neurotransmission within the C-fibers caused by cervical disc pathology are thought to produce and worsen the pain in CGH.
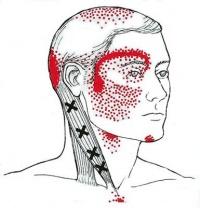
The trigeminocervical nucleus receives afferents from the trigeminal nerve and the upper 3 cervical spine nerves. Neck trauma, whiplash, strain or chronic spasm of the scalp, neck or shoulder muscles can increase the area`s sensitivity similar to the allodynia seen in chronic migraines. A lower pain threshold makes patient more susceptible to more severe pain. For this reason, early diagnosis and therapeutic intervention are very important.
About 70% of CGH cases involve pathology of C2-3 zygapophyseal joint.
What is the epidemiology of CGH?
CGH is a rare condition that appears in people between the age of 30-44 years. Its prevalence among patients with headaches is 0.4 to 4 % affecting males and females nearly equally with the ratio of 0.97 (F/M). (https://www.ncbi.nlm.nih.gov/books/NBK507862/#:~:text=A%20cervicogenic%20headache%20presents%20as,of%20motion%20of%20the%20neck.)
What are the symptoms of CGH?
One sign of CGH is pain that comes from a sudden movement of neck. Another is, a headache that comes from the neck remaining in the same position for some time. Other signs may include:
- Pain on one side of head or face
- Steady pain that doesn`t throb
- Head pain while coughing, sneezing or taking a deep breath
- An attack of pain that can last for hours or days
- Stiff neck with restricted movements
- Pain that keeps coming in one spot, like the back, front or side of head or around the eye (https://www.webmd.com/migraines-headaches/cervicogenic-headache-facts_)
What causes CGH?
Because CGH arise from problems in the neck region, different conditions can trigger this type of pain. These include:
- Osteoarthritis of the neck
- Prolapsed disk in the neck
- Whiplash injury
- Falling down or contact sport injury
- Sustained improper posture while sitting or standing at work
- Jobs involving too much poker chin posture such as driving, carpentry, hair stylist
- Trapped nerve in cervical spine
- Falling asleep in awkward position (https://www.healthline.com/health/headache/cervicogenic-headache#causes)
How is CGH diagnosed?
History of patient`s symptoms is taken followed by physical examination of the head and neck. Range of movements are tested to reveal restrictions and stiffness. Patient is less likely to complain about sensitivity to light or noise such as in migraine.
Manual assessment of the upper cervical segmental mobility and pain has good reliability, with positive findings (pain produced with passive mobilization) in 63% of CGH patients and sensitivity of 80% as per study done by Page in 2011. (https://www.ncbi.nlm.nih.gov/pmc/articles/PMC3201065/)
Imaging of the cervical spine is not sensitive enough to diagnose CGH. MRI, CT or CT myelography can be ordered to rule out Chiari malformations, nerve root pathology assessment or identify spinal cord pathology.
The ICHD-3 criteria for cervicogenic headache are as follows:
- Any headache fulfilling criterion C
- Clinical and/or imaging evidence of a lesion or disorder in the cervical spine or soft tissues of the neck that can cause a headache
- Evidence of cause of headache demonstrated by at least 2 of the following:
- Headache has developed in temporal relation to the appearance of the lesion or the onset of the cervical disorder
- Headache has significantly improved or resolved in unison with improvement in or the resolution of the cervical lesion or disorder
- Cervical range of motion is reduced, and provocative manoeuvres may significantly worsen the headache
- Headache is abolished following diagnostic blockade of a cervical structure or its nerve supply
- Not better accounted for by another ICHD-3 diagnosis
Diagnostic anaesthetic blocks can sometimes be utilized to confirm the diagnosis but require specialized skills and are not routinely performed.
What is the treatment for CGH?
- Medicine: non-steroidal anti-inflammatories (aspirin or ibuprofen), muscle relaxants or other pain relievers may help with pain relief.
- Physical therapy is usually considered as first line of treatment. Manipulative therapy and therapeutic exercise regimens are effective in treating a cervicogenic headache. According to a study by Jull and Richardson, 72% of patients had reduced 50% or more in headache frequency at the 12-month follow-up, and 42% of patients reported 80% or higher relief of some sort. These manipulative manoeuvres stimulate neural inhibitory systems at various levels in the spinal cord and activate descending inhibitory pathways.
- Other non-surgical ways to deal with CGH include relaxation technique like deep breathing, yoga or acupuncture. (https://www.webmd.com/migraines-headaches/cervicogenic-headache-facts)
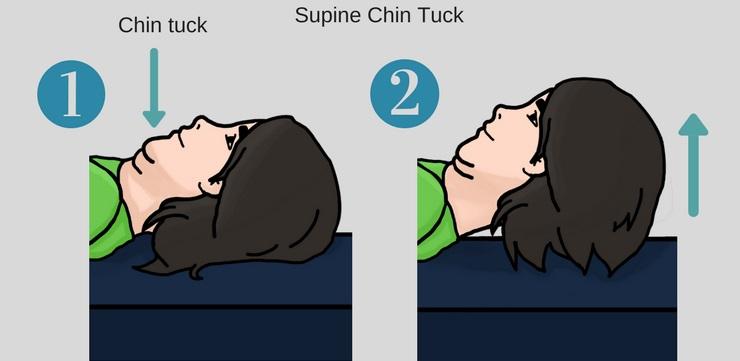
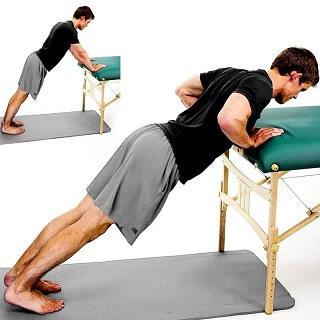
Strengthening of deep neck flexors and scapular stabilizer exercises, in addition to upper cervical extensor stretching are advocated in the treatment of CGH. (https://www.ncbi.nlm.nih.gov/books/NBK507862/#:~:text=A%20cervicogenic%20headache%20presents%20as,of%20motion%20of%20the%20neck.)
Nerve block: this may temporarily relieve pain and help work with physical therapy.